 View full size ↗
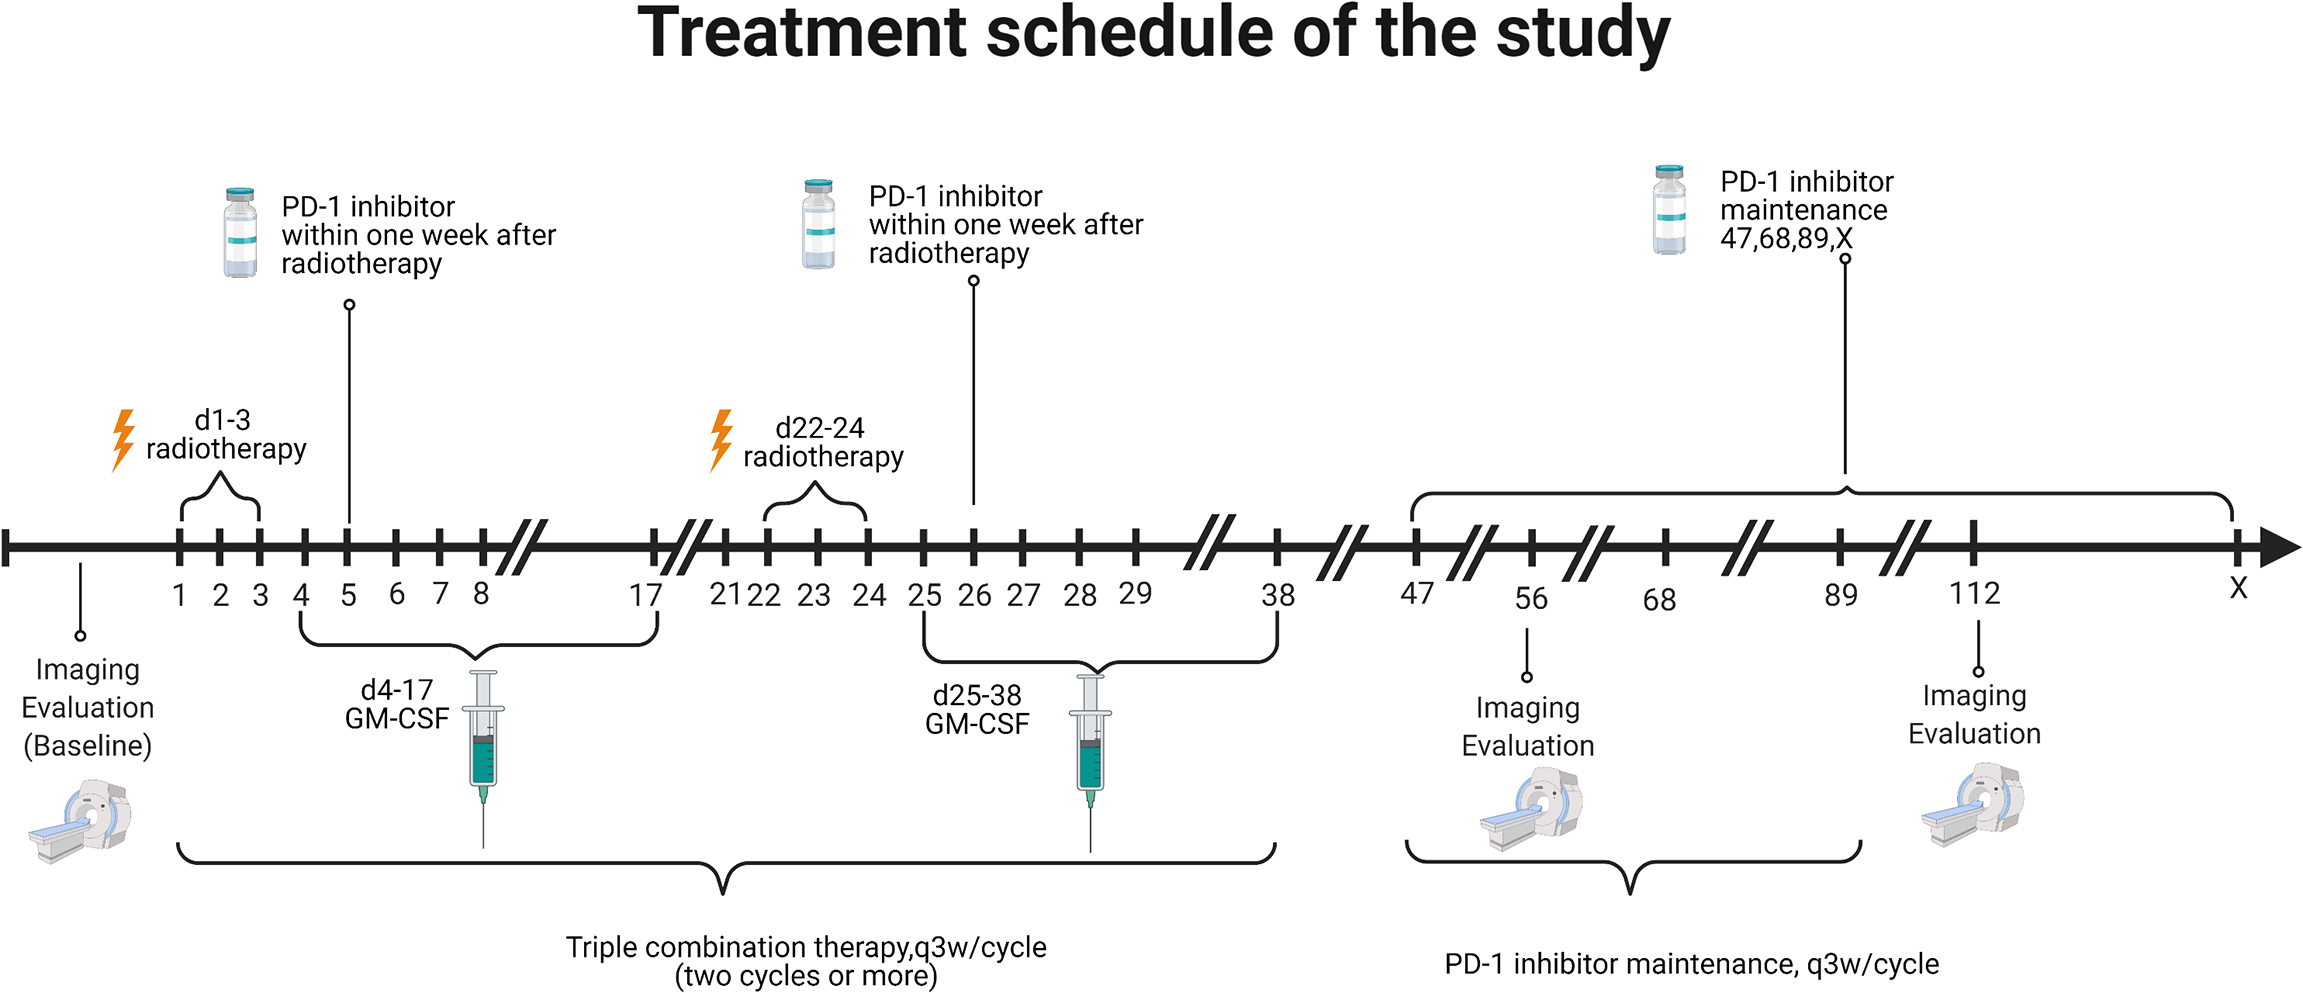
Read from left to right: repeated radiotherapy and immune-treatment cycles were followed by maintenance treatment and imaging assessments. This is the schedule of the 2022 study, rather than a universal schedule for every PRaG-derived approach.
© 2022 Kong et al. · Frontiers in Immunology, 2022 · Figure 1 · CC BY 4.0. Reproduced without alteration.
In plain language
A clinical study can offer a reason to investigate a treatment without settling whether it is better than existing care. The 2022 PRaG paper is useful to read in exactly this way: as an early prospective evaluation of a three-part strategy in people whose metastatic cancers had resisted previous treatment.
The study in context
The report enrolled 54 patients and combined PD-1 inhibition, radiotherapy and GM-CSF. It measured tumor response as its primary endpoint. The published objective response rate was 16.7% in the intention-to-treat population. This is a measure of tumor shrinkage meeting defined criteria, not a cure rate.
Median progression-free survival was 4.0 months and median overall survival was 10.5 months. These are cohort summaries; they cannot forecast an individual patient’s experience.
What the design cannot answer
There was no randomized comparison group. Differences in cancer type, prior treatment and health status make comparison with unrelated studies unreliable. The results cannot show how much benefit came from each of the three components or establish superiority over standard care.
Safety belongs in the same conversation
The paper reported grade 3 and grade 4 treatment-related adverse events. Earlier triplet experience also included a case with severe pneumonia. A response and a serious adverse event can both be true; careful reporting keeps both visible.
Questions to carry forward
- Which patient groups are most likely to benefit?
- How do different radiation strategies affect outcomes and toxicity?
- Can a controlled trial separate treatment effects from selection effects?
- Are later regimens supported by completed results or only by a proposed protocol?
The publication page links to the original source and separates the cohort’s findings from these unresolved questions.
 View full size ↗
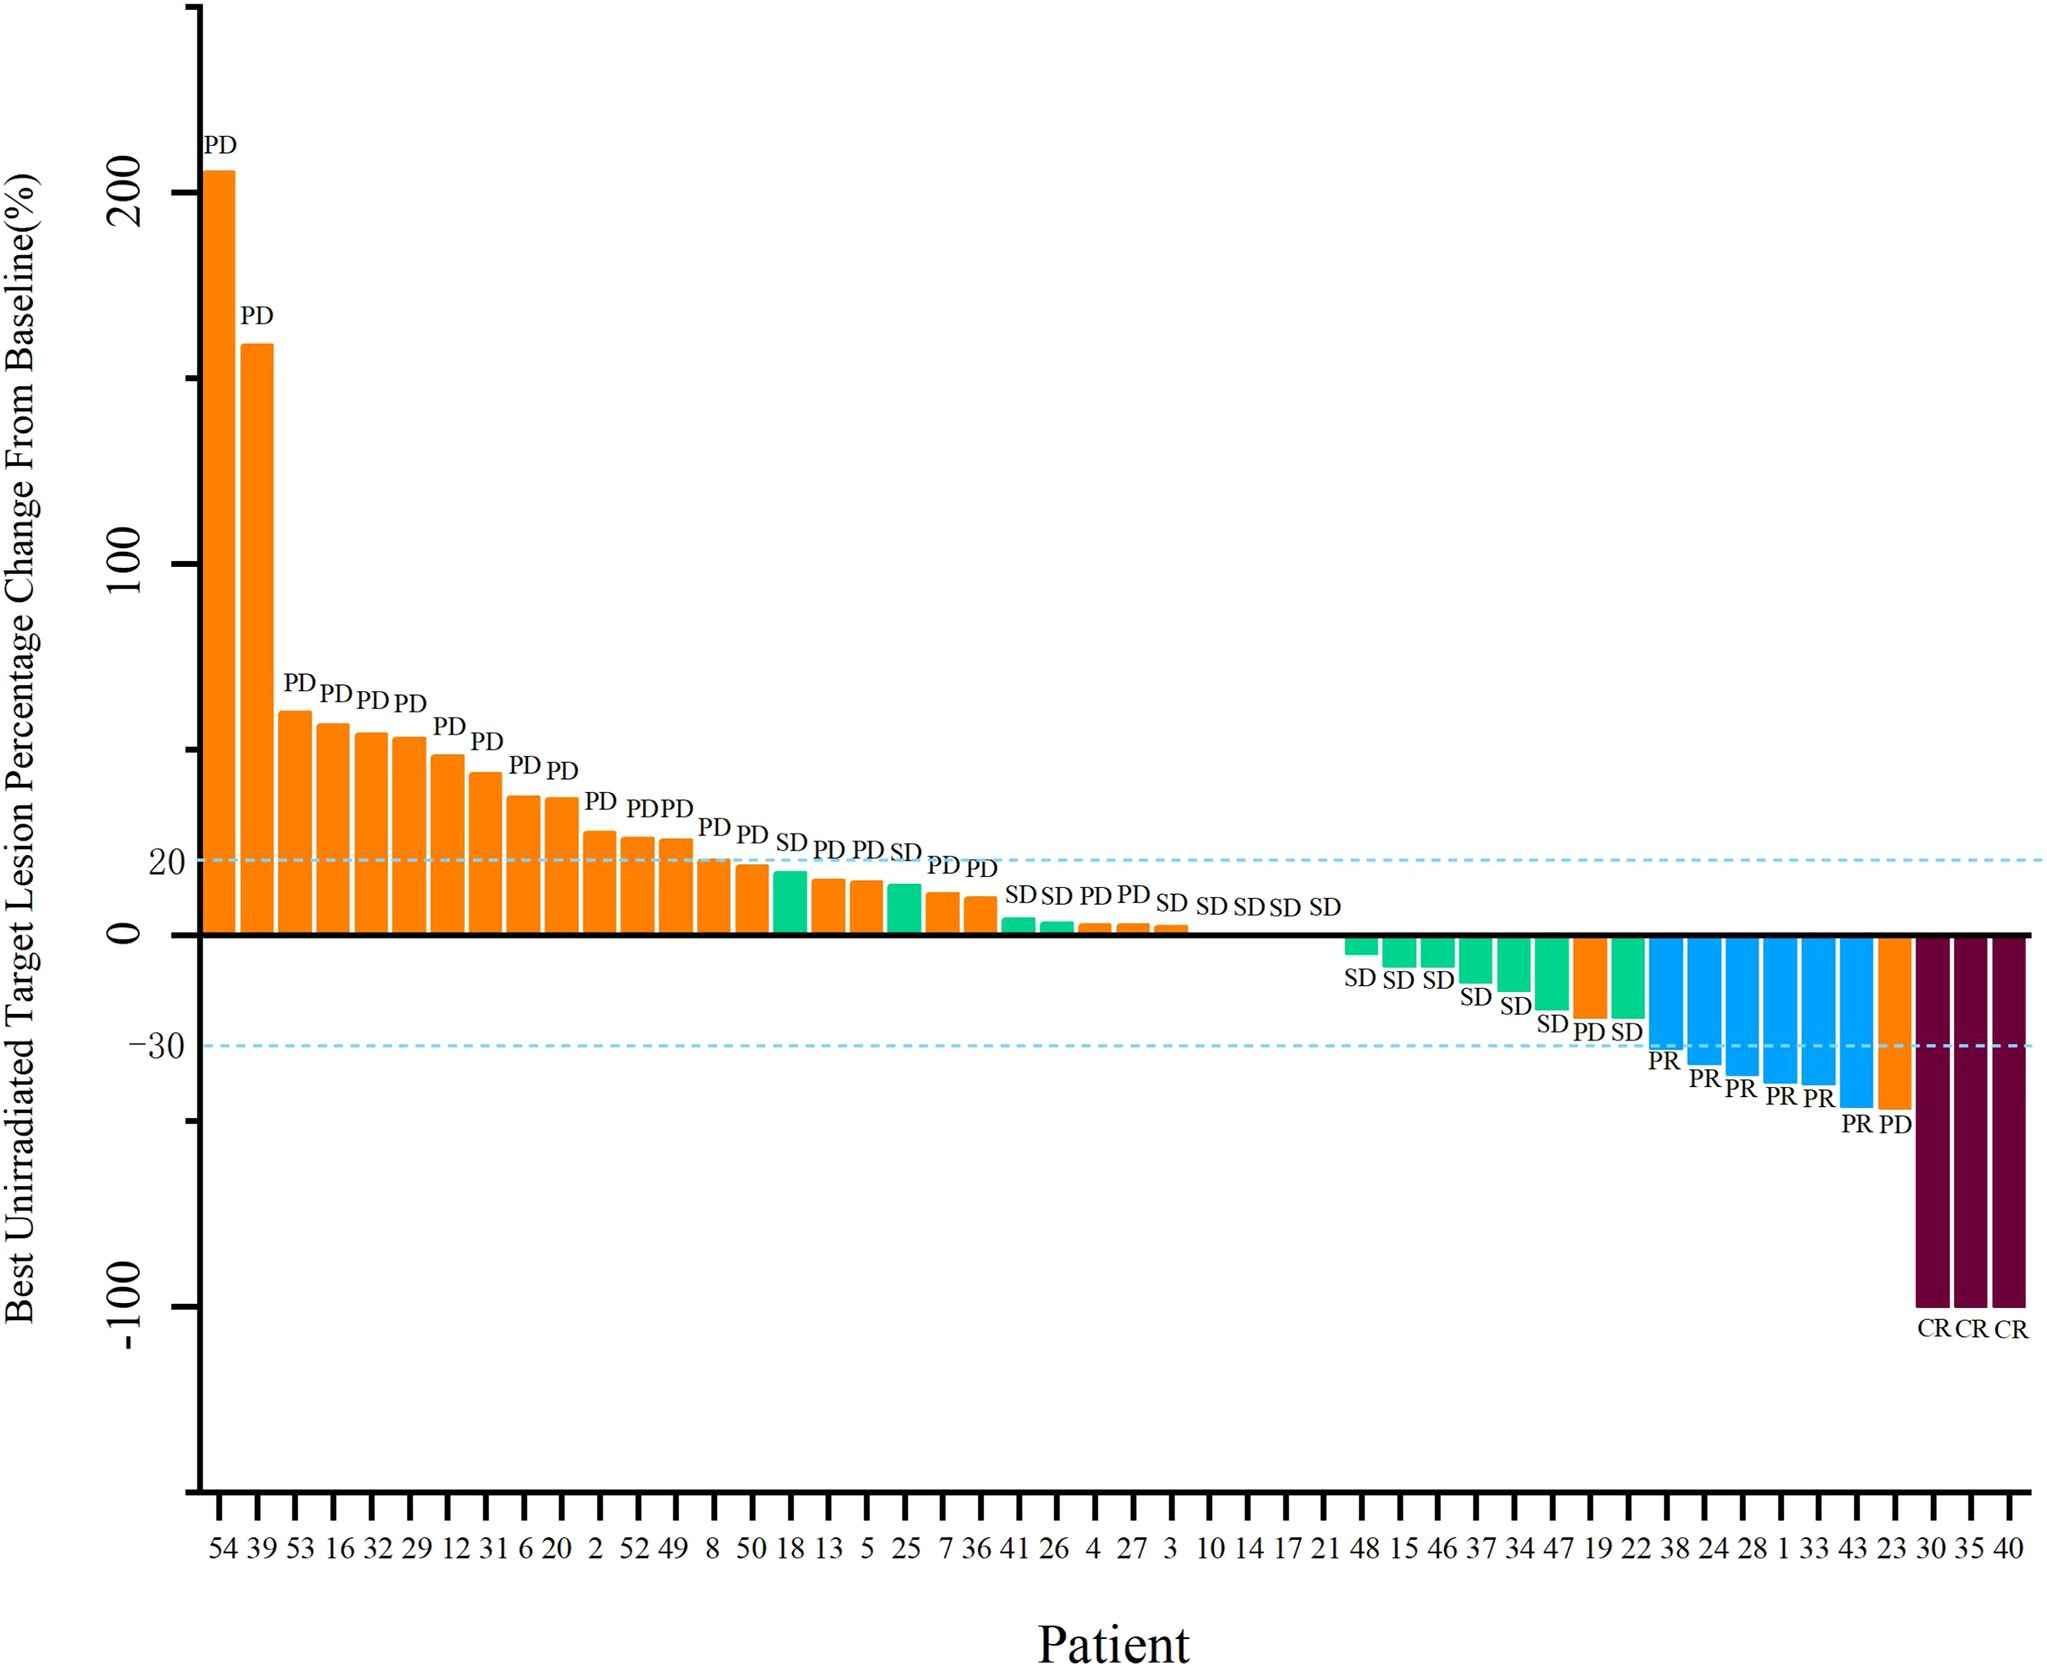
Each bar represents one response-evaluable patient. Bars below zero show shrinkage of nonirradiated target lesions; bars above zero show growth. Both responses and progression are visible. CR, PR, SD and PD denote the authors’ response categories; this uncontrolled study cannot establish superiority over another treatment.
© 2022 Kong et al. · Frontiers in Immunology, 2022 · Figure 3 · CC BY 4.0. Reproduced without alteration.
Sources and related publications
- PD-1 Inhibitor Combined With Radiotherapy and GM-CSF (PRaG) in Patients With Metastatic Solid Tumors: An Open-Label Phase II Study · Original source ↗
- Anti-PD-1 Immunotherapy Combined With Stereotactic Body Radiation Therapy and GM-CSF as Salvage Therapy in a PD-L1-Negative Patient With Refractory Metastatic Esophageal Squamous Cell Carcinoma: A Case Report and Literature Review · Original source ↗